Anemia is often associated with iron deficiency, but low haemoglobin level does not automatically mean that your body lacks iron.
There are several different causes of anemia, and identifying the underlying cause is important before starting treatment. This is particularly relevant in Malaysia, as thalassaemia is an important cause of low haemoglobin or small red blood cells and may sometimes resemble iron deficiency on an initial blood test.
What Is Anemia?
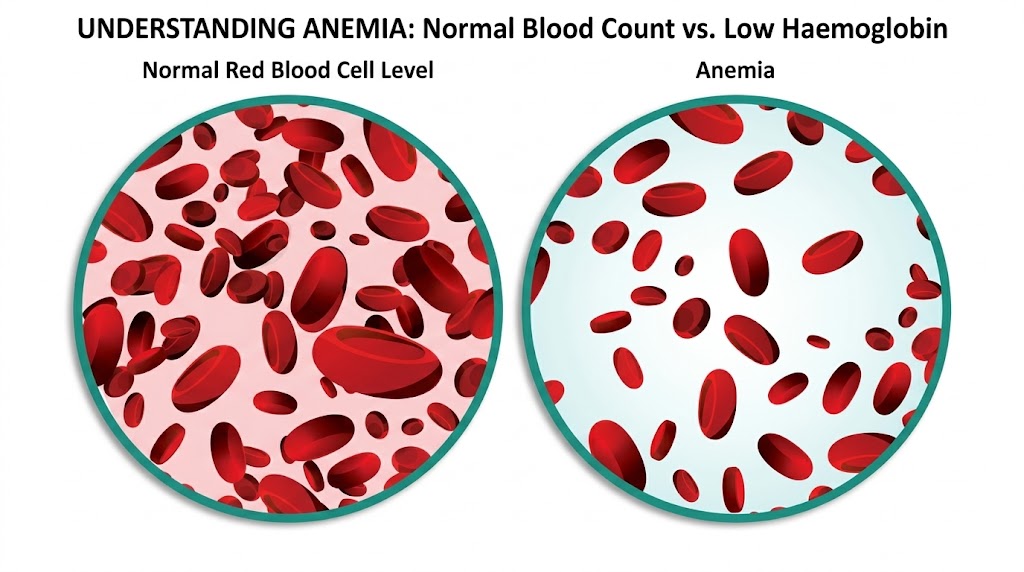
Anemia occurs when the blood does not have enough haemoglobin or healthy red blood cells to adequately carry oxygen around the body.
Common symptoms include:
- Tiredness or weakness
- Dizziness or light-headedness
- Shortness of breath, especially during activity
- Palpitations or a faster heartbeat
- Headaches
- Pale skin
- Reduced exercise tolerance
However, mild anemia may cause few or no noticeable symptoms and may only be discovered during a routine blood test.
7 Important Causes of Anemia You Should Know
1. Iron Deficiency Anemia
Iron is needed to produce haemoglobin. When the body’s iron stores become depleted, it may eventually lead to iron deficiency anemia.
Possible reasons include:
- Heavy or prolonged menstrual bleeding
- Inadequate dietary iron intake
- Pregnancy and increased iron requirements
- Gastrointestinal blood loss
- Problems affecting iron absorption
Identifying why someone is iron deficient is also part of proper assessment particularly when the deficiency is persistent or recurrent.
2. Thalassaemia
Thalassaemia is an inherited blood disorder that affects haemoglobin production. It is particularly important to consider in Malaysia.
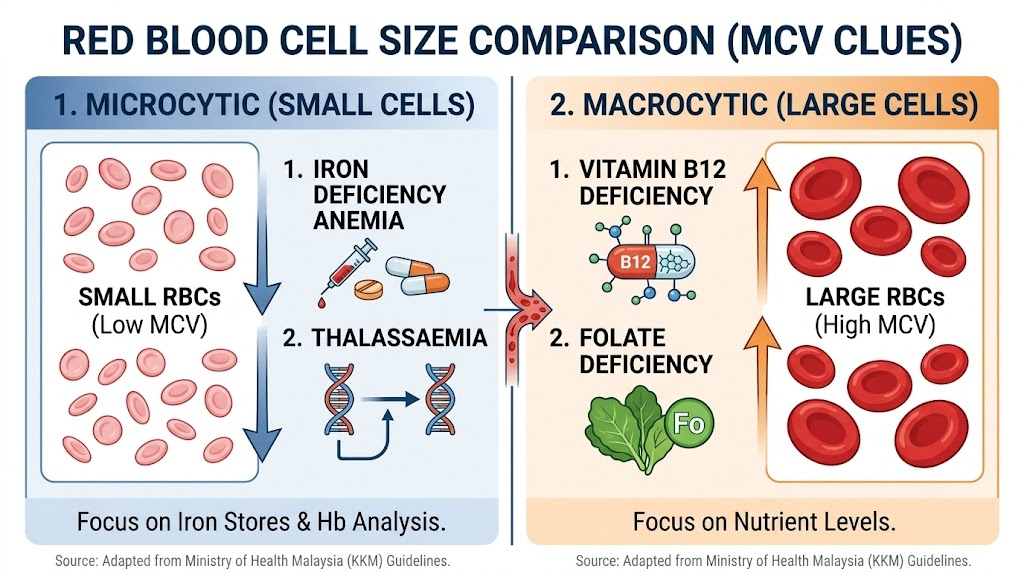
A person with a thalassaemia trait or carrier state may have small red blood cells, reflected by a low mean corpuscular volume (MCV) or mean corpuscular haemoglobin (MCH), even when iron deficiency is not the explanation.
Malaysia’s Ministry of Health (KKM) thalassaemia guidance incorporates full blood count (FBC), peripheral blood film and haemoglobin analysis into the assessment and screening pathway for suspected thalassaemia.
3. Vitamin B12 or Folate Deficiency
Your body also needs vitamin B12 and folate to produce healthy red blood cells.
Deficiency may develop because of inadequate intake, increased requirements or conditions that interfere with nutrient absorption.
Unlike the typically smaller red blood cells associated with iron deficiency, vitamin B12 or folate deficiency may be associated with larger-than-normal red blood cells.
4. Chronic Disease or Inflammation
Long-term inflammatory or chronic medical conditions can interfere with the production and regulation of red blood cells and iron.This means a patient may develop anemia even when inadequate dietary iron is not the primary problem.
5. Kidney Diseases
The kidneys help regulate red blood cell production through a hormone called erythropoietin.
When kidney function becomes significantly impaired, erythropoietin production may decrease and contribute to anemia. Kidney function tests may therefore form part of the investigation when clinically appropriate.
6. Blood Loss
Blood loss is another important cause of anemia.
It may be obvious, such as heavy menstrual bleeding, but sometimes blood loss can be less noticeable. Depending on the person’s age, symptoms and medical history, a doctor may need to consider sources of bleeding from the gastrointestinal or other systems.
This is particularly important when iron deficiency is persistent, recurrent or has no obvious explanation.
7. Other Blood and Bone Marrow Disorders
Less commonly, anemia may result from conditions affecting the production, lifespan or destruction of red blood cells.
These can include haemolytic disorders, bone marrow conditions and other haematological diseases.
These conditions cannot be diagnosed based on haemoglobin alone and may require additional blood investigations or specialist assessment.
Feeling tired is also not specific to anemia, you may also read other causes of persistent tiredness: Always Feeling Tired? 8 Common Causes and When to See a Doctor on our blog!
Anemia Workup: Investigations for Anemia
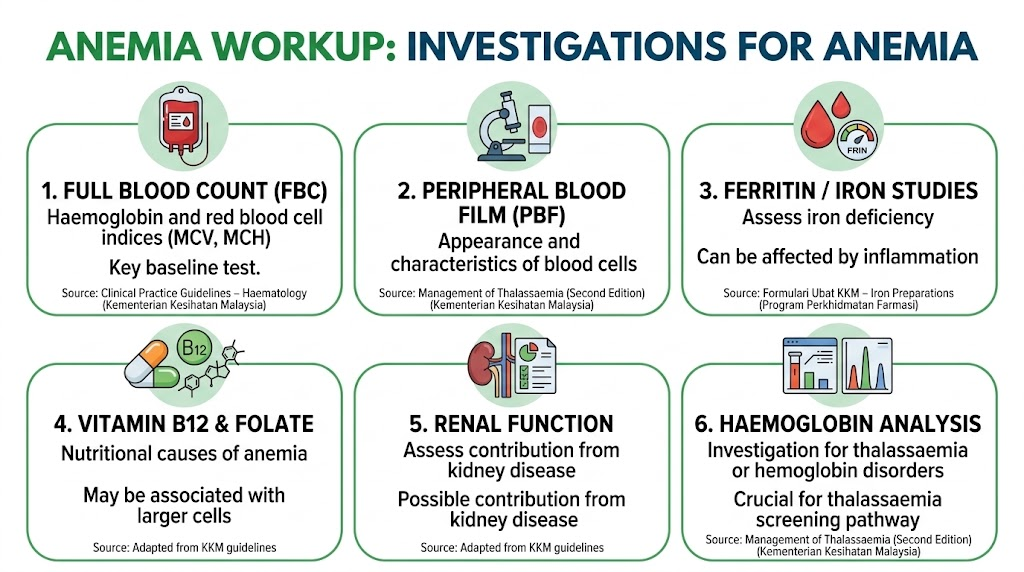
An anemia workup aims to determine the underlying reason for a low haemoglobin level rather than assuming that every case is caused by iron deficiency.
The investigations required will differ from person to person. Depending on the clinical findings, a doctor may consider:
| Investigation | What It May Help Assess |
| Full Blood Count (FBC) | Haemoglobin and red blood cell indices such as MCV and MCH |
| Peripheral Blood Film (PBF) | Appearance and characteristics of blood cells |
| Ferritin / iron studies | Whether iron deficiency is likely |
| Vitamin B12 and folate | Nutritional causes of anemia |
| Reticulocyte count | How the bone marrow is responding to anemia |
| Renal function | Possible contribution from kidney disease |
| Liver function | Associated liver disease or other contributing conditions |
| Haemoglobin analysis | Investigation for thalassaemia or certain haemoglobin disorders |
| Other targeted investigations | May be required depending on symptoms, examination and suspected cause |
Not everyone with anemia needs every test on this list. Investigations should be selected based on the person’s FBC pattern, symptoms, medical and family history, physical examination and suspected underlying cause.
KKM’s current thalassaemia guidance specifically supports further assessment when red-cell indices raise suspicion of thalassaemia, rather than treating all microcytic presentations as iron deficiency.
References: Ministry of Health Malaysia (Kementerian Kesihatan Malaysia) & Pharmaceutical Services Programme (Program Perkhidmatan Farmasi).
Why Ferritin Can Be Important Before Taking Iron
A Full Blood Count can identify anemia and provide useful clues about its cause, but it does not by itself confirm iron deficiency.
Ferritin is commonly used to assess the body’s iron stores. However, ferritin can also be affected by inflammation and other medical conditions, which means the result needs to be interpreted together with the patient’s clinical situation and, when necessary, other iron studies.
For this reason, self-treating a low haemoglobin level with iron supplements without determining the cause may not always be appropriate.
KKM’s formulary specifically lists oral iron preparations for the prevention and treatment of iron-deficiency anaemia, reinforcing that iron therapy has a defined indication rather than being a universal treatment for every type of anemia.
Iron Deficiency vs Thalassaemia: Why the Difference Matters
Both iron deficiency and thalassaemia can produce small red blood cells, so they can sometimes appear similar on an initial FBC. However, their management is different.
Iron deficiency requires identification and correction of the iron deficiency as well as consideration of its underlying cause. Thalassaemia is an inherited haemoglobin disorder and may require haemoglobin analysis, counselling or further specialist assessment depending on the type and severity.
The Ministry of Health Malaysia’s thalassaemia screening algorithm includes FBC assessment followed, where indicated, by further testing such as peripheral blood film and haemoglobin analysis.
Should You Take Iron Supplements Whenever Your Haemoglobin Is Low?
Not automatically.
Iron supplementation may be appropriate when iron deficiency has been identified or when prescribed for a specific clinical indication. However, if another condition is causing the anemia, iron may not address the underlying problem.
If you have been told that your haemoglobin is low, it is reasonable to discuss with your doctor whether further investigation is needed before starting or repeatedly taking iron supplements.
When Should You See a Doctor for Anemia?
Arrange a medical assessment if you have
- Persistent tiredness
- Unexplained weakness
- Dizziness
- Palpitations
- Shortness of breath
- Unusually heavy menstrual bleeding
- Previously been told that your haemoglobin is low.
Seek urgent medical attention if symptoms are severe, particularly if you develop significant shortness of breath, chest pain, fainting, severe weakness or active/heavy bleeding.
The urgency of anemia depends not only on the haemoglobin result but also on the person’s symptoms, underlying condition and how quickly the anemia developed.
Anemia Testing in Malaysia: Finding the Cause Matters
For patients in Malaysia, anemia should not automatically be assumed to be caused by iron deficiency. Iron deficiency, thalassaemia, nutritional deficiencies, chronic illnesses, kidney disease, blood loss and other blood disorders can all contribute to a low haemoglobin level.
A proper medical assessment can help determine which investigations are appropriate and whether treatment is necessary.
At Klinik Central SS15, Subang Jaya and Klinik Central Taman Megah, Petaling Jaya, patients with suspected anemia can speak to a doctor about their symptoms and appropriate blood investigations. Further investigations or specialist referral can be arranged when clinically indicated.
Frequently Asked Questions About Anemia
Is all anemia caused by iron deficiency?
No. Iron deficiency is only one cause. Anemia may also be related to thalassaemia, vitamin B12 or folate deficiency, chronic disease, kidney disease, blood loss and other blood disorders.
Can I have low haemoglobin even if my iron level is normal?
Yes. A person can have anemia for reasons unrelated to iron deficiency. Further assessment may be required to identify the cause.
Does low MCV always mean iron deficiency?
No. A low MCV means that the red blood cells are smaller than usual. Iron deficiency is one possible cause, but thalassaemia is another important consideration, particularly in Malaysia.
What blood tests are commonly used to investigate anemia?
An FBC is usually an important starting point. Depending on the results and clinical history, further investigations may include ferritin or iron studies, peripheral blood film, vitamin B12, folate, reticulocyte count, renal function and haemoglobin analysis.
Should I take iron supplements if I am anemic?
Not automatically. Iron treatment is appropriate for iron deficiency and certain specific clinical situations. The underlying cause of anemia should be considered before assuming iron is required.
Can thalassaemia be mistaken for iron deficiency?
They can share certain blood-test features, particularly small red blood cells. Further investigations such as iron assessment and haemoglobin analysis can help distinguish between them when clinically indicated.
The Key Message
Low haemoglobin does not automatically mean iron deficiency.
A low haemoglobin result is the beginning of the investigation—not necessarily the final diagnosis. Understanding whether anemia is caused by iron deficiency, thalassaemia, nutritional deficiency, chronic disease, blood loss or another condition allows treatment to be directed at the actual cause.
If you have persistent symptoms or an abnormal blood test, speak to a healthcare professional for appropriate assessment rather than starting iron supplements on your own.
References
- Ministry of Health Malaysia. Management of Thalassaemia (Second Edition). 2024. (Kementerian Kesihatan Malaysia)
- Ministry of Health Malaysia. Clinical Practice Guidelines – Haematology. The current KKM CPG directory lists Management of Thalassaemia (Second Edition) among its haematology guidelines. (Kementerian Kesihatan Malaysia)
- Ministry of Health Malaysia. Management of Transfusion Dependent Thalassaemia – screening algorithm incorporating FBC, MCH, peripheral blood film and haemoglobin analysis. (Kementerian Kesihatan Malaysia)
- Pharmaceutical Services Programme, Ministry of Health Malaysia. Formulari Ubat KKM – Iron Preparations. (Program Perkhidmatan Farmasi)